People with kidney failure need a reliable way into the bloodstream for dialysis. An AV fistula, made by a vascular surgeon, is the most reliable option for long-term hemodialysis. When a fistula is not possible, an AV graft or a permacath is used instead.
Medically reviewed by Dr. Aniruddha Bhuiyan, MCh vascular surgeon. Updated October 2026.
Dialysis access: understanding AV fistula, AV grafts and permacath
For people with kidney failure, dialysis becomes part of daily life. It removes waste and extra fluid from the body when the kidneys can no longer do it. To work well, dialysis needs a safe and reliable way into the bloodstream, called dialysis access.
So making that access is the job of dialysis access surgery. As vascular surgeons, we create these access points and also keep them working. The first choice is an arteriovenous (AV) fistula. When a fistula is not possible, we use an AV graft or a permacath (a tunnelled catheter).
Permacath or AV fistula, which is better? For long-term dialysis, an AV fistula is the better choice. It uses your own blood vessels, lasts the longest and has the lowest risk of infection, but it needs about 4 to 8 weeks to mature before it can be used. A permacath works the same day, so doctors use it when dialysis is urgent or while a fistula matures. Because a permacath carries a higher risk of infection and blockage, it is best kept as a short-term bridge. An AV graft sits in between and can usually be used within 2 to 3 weeks. See the full comparison.
What is an AV fistula?
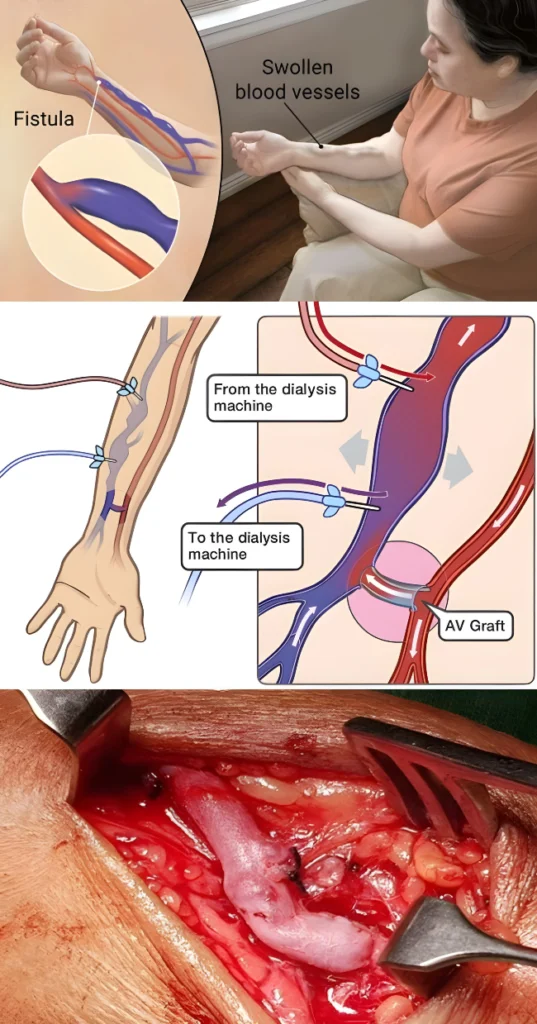
An AV fistula is a direct surgical join between an artery and a vein, usually in the arm. It is the gold standard for hemodialysis because it uses your own blood vessels. That makes it last longer and cause fewer problems.
The procedure is short, and the surgeon does it under local anesthesia. After surgery, the fistula then takes about 4–8 weeks to mature. In that time the vein grows thicker and stronger, so it can take repeated needles during dialysis.
Why is an AV fistula preferred?
Kidney specialists and surgeons around the world recommend the AV fistula as the first choice for long-term dialysis. The NHS gives a simple overview of how dialysis works.
Key benefits
Benefit
Description
Long-lasting
Can function for years if well maintained.
No artificial material
Made from your body’s natural tissues.
Lower infection risk
Much safer than artificial access.
Less risk of clotting
Blood flow remains steady.
Faster and more efficient dialysis
Better clearance during sessions.
Fewer hospital visits
Less prone to emergencies compared to other options.
How is an AV fistula created?
First, the surgeon carefully checks your blood vessels:
Clinical examination by the vascular surgeon.
Ultrasound (Doppler study): a painless scan that measures the size and quality of your veins and arteries.
Doctors call this vessel mapping or vessel planning. It also tells us the best place for your fistula, usually the forearm or upper arm.
Once the surgeon chooses the right spot:
The surgeon works under local anesthesia.
Through a small cut, the surgeon connects a nearby artery to a vein.
As a result, more blood flows into the vein, making it larger and stronger.
Following surgery, the fistula needs 4 to 8 weeks to mature. During this time:
The vein walls thicken.
Blood flow increases.
Dialysis nurses can also feel a vibration (called a thrill) over the site.
When the fistula has matured, two needles go into it at each dialysis session. One takes blood out, while the other returns it after filtering.
Challenges with AV fistula
Some patients cannot have a fistula because of:
Small or weak veins
Prior surgeries or injuries to the arm
Multiple failed fistulas
Advanced age or fragile vessels
For them, we look at the other options below instead.
What if an AV fistula is not possible?
AV graft
When your veins are not suitable for a fistula, the next best option is an AV graft.
An AV graft is a soft synthetic tube, made of a medical material called PTFE, that joins an artery to a vein, usually in the upper arm. It acts as a bridge for blood flow, so the dialysis needles go into it just as they would into a fistula.
Features of an AV graft
Used when veins are unsuitable
Ready for use within 2–3 weeks after surgery
Inserted between an artery (elbow level) and a vein (shoulder level)
Easier to place, especially in elderly or obese patients
Things to watch out for
Slightly higher risk of infection compared to AV fistula
May develop clots or narrowing more frequently
Needs more frequent monitoring
Still, with good care and regular check-ups, an AV graft can work well for a long time.
Permacath (Permcath): tunnelled dialysis catheter
Doctors use a permacath when the arms cannot take a fistula or graft, or when the patient needs dialysis straight away.
It is a soft plastic tube placed in a large vein in the chest or thigh, with its tip close to the heart. It runs in a tunnel under the skin, which holds it steady and lowers the risk of infection compared with temporary catheters.
When doctors use permacaths
Emergency dialysis without time for a fistula to mature
Vein access not possible in arms
As a bridge to AV fistula/graft in patients with complex medical conditions
Risks of permacath
Higher chance of infection
Can block or malfunction over time
Not ideal for long-term use unless no other access is available
A permacath is a temporary or in-between solution, so we avoid it as a long-term option when we can.
Which dialysis access is right for you?
Every patient is different. The choice depends on:
Vein size and quality
Medical condition
Urgency of dialysis
Prior surgeries or failed access
Expected duration on dialysis
Permacath vs AV fistula vs AV graft: which is better?
Feature
AV Fistula
AV Graft
Permacath
Material
Natural (your veins)
Synthetic tube
Plastic catheter
Infection Risk
Low
Moderate
High
Longevity
Longest
Moderate
Short-term
Time to Use
4–8 weeks
2–3 weeks
Immediate
Insertion Site
Forearm/arm
Arm
Chest/thigh
Best For
Long-term dialysis
Poor veins
Urgent use or no access
Caring for your dialysis access
Whatever type of access you have, good daily care prevents most problems, so the habits below matter.
Do:
Avoid
Keep the area clean and dry
Check daily for swelling, redness, or bleeding
Wash hands before touching the site
Inform your dialysis team about any changes
Sleeping on the access arm
Wearing tight clothes over the site
Allowing blood pressure or IVs on that arm (for fistula/graft)
We may also check the access with ultrasound from time to time, to see how well it is working and to catch narrowing before it blocks.
Why choose a vascular surgeon for dialysis access?
Creating and maintaining high-quality, durable access
Managing complications like blockage, infection, bleeding, or failure
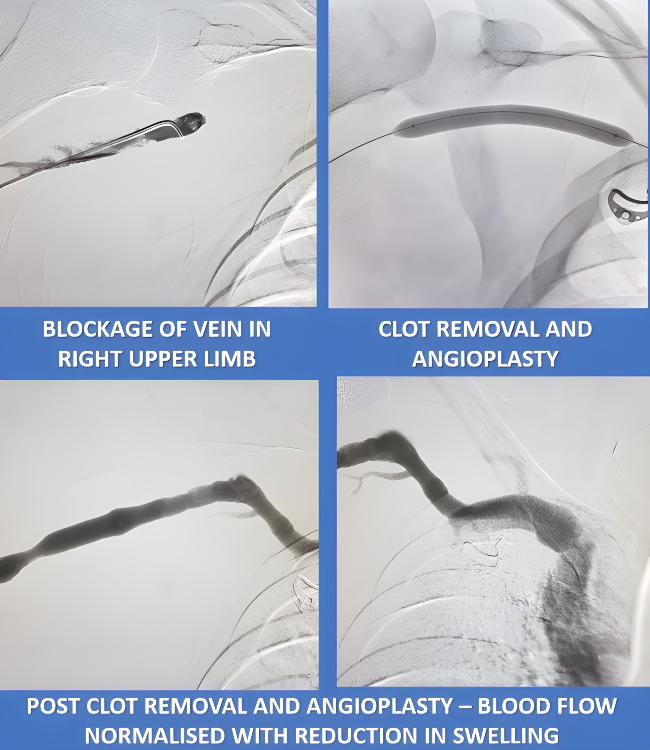
Treating problems with balloon angioplasty, thrombectomy or stent placement when needed
We want your access to last as long as possible, with few complications and smooth dialysis sessions.
Frequently asked questions
Why is an AV fistula preferred?
The surgeon makes it from your own artery and vein, so it lasts longer and carries a lower risk of infection and clotting than an AV graft or a permacath.
How soon can a new fistula be used for dialysis?
Usually after 4 to 8 weeks, once the vein has grown thicker and stronger. An AV graft is usually ready within 2 to 3 weeks.
Is the operation done under general anaesthesia?
No. The surgeon usually makes a fistula under local anaesthesia through a small cut in the arm.
How do I look after my fistula?
Keep the area clean and dry and check it daily for swelling, redness or bleeding. Do not sleep on that arm or wear tight clothing over it, and do not allow blood pressure readings or IV lines in that arm.
Permacath vs AV fistula: which is better?
For long-term dialysis, an AV fistula is better than a permacath. It uses your own artery and vein, lasts longer and has a much lower risk of infection and blockage. A permacath is useful when you need dialysis straight away or when a fistula is not possible, but it works best as a bridge until a fistula or graft is ready.
How long does a permacath last?
A permacath can work for several months, sometimes longer. But the longer it stays in, the higher the risk of infection, blockage and narrowing of the vein it sits in. That is why we plan a fistula or graft early, so the catheter can come out as soon as possible.
How is a permacath inserted?
The surgeon places it under local anaesthesia, usually through the large vein in the neck (the internal jugular vein), with ultrasound guiding the needle. The catheter runs in a tunnel under the skin so it comes out on the upper chest, and a small cuff under the skin holds it in place and helps keep out infection. An X-ray then confirms the tip sits just above the heart. The procedure usually takes under an hour, and dialysis can start through the catheter the same day.
Does a permacath have a thrill?
No. A thrill is the buzzing vibration you can feel over a working fistula or graft, caused by fast blood flow from the artery into the vein. A permacath is a tube inside a vein, so there is no thrill. If a fistula or graft loses its thrill, it may have clotted and needs urgent review.
What is AVG in dialysis?
AVG stands for arteriovenous graft: a soft synthetic tube placed under the skin of the arm to join an artery to a vein. The dialysis needles then go into the tube. Surgeons use it when the veins are too small or damaged for a fistula, and it is usually ready 2 to 3 weeks after surgery.
AV fistula vs AV graft: which is better?
A fistula is better when your veins allow it, because it lasts longer and has fewer infections and blockages. A graft is the next choice when the veins are not suitable, and it is ready sooner.
Is a chest catheter the same as a fistula?
No. The tube in the chest is a permacath, a tunnelled catheter in a large vein. A fistula, however, is a joint between your own artery and vein, usually in the arm. People sometimes call the chest catheter a “chest fistula”, but a fistula is the better long-term option.
Can dialysis be done without a fistula?
Yes. Dialysis can start through a permacath while the surgeon makes a fistula or graft, and patients who cannot have a fistula can use a graft. Also, peritoneal dialysis, done through a tube in the abdomen, needs no fistula at all.
Dialysis access is not just an operation. It is a lifeline.
Dialysis access: plan it early
A well-planned access means smoother dialysis, fewer hospital stays and a better quality of life. If you or someone in your family is preparing for dialysis, see a vascular surgeon early. We will help you plan it safely, with the best long-term results in mind.